


Clinicians Corner, from Critical Care Medicine, explores a patient case that has sparked debate. This interactive series allows you to review the case details, vote on how you would treat the patient, and see how current poll results are trending after you submit. Then watch for an email with access to the Critical Care Medicine article featuring in-depth perspectives on the case by critical care experts.
Look for the next poll soon!
A 54-year-old woman with diabetes and on insulin presents to the emergency department with a 2-day history of cough productive of yellow-green sputum and increasing respiratory distress. On arrival, temperature is 40 °C (104 °F), blood pressure 80/55 mm Hg, heart rate 125 beats/min, respiratory rate 36 breaths/min, and oxygen saturation 85% via 6 L nasal cannula. Chest radiograph shows diffuse bilateral infiltrates that are greater on the right than the left. The patient is administered 2 L of crystalloid and started on antibiotics appropriate for community-acquired pneumonia. For increasing shortness of breath, she is treated with a heated high-flow nasal cannula but has no improvement in respiratory distress or saturation. Thus, the patient is intubated at FIO2 0.7 and positive end-expiratory pressure (PEEP) at 8 cm H2O. Arterial blood gas analysis shows pH 7.38, PCO2 41 mm Hg, and PaO2 68 mm Hg, with tidal volume 6 mL/kg ideal body weight. Peak pressure is 24 cm H2O and plateau pressure is 22 cm H2O.
Which of the following is the most appropriate next step in managing the PEEP and FIO2?
Here’s how your peers responded:

Read the research: Clinicians Corner: Setting Positive End-Expiratory Pressure in the Acute Respiratory Distress Syndrome
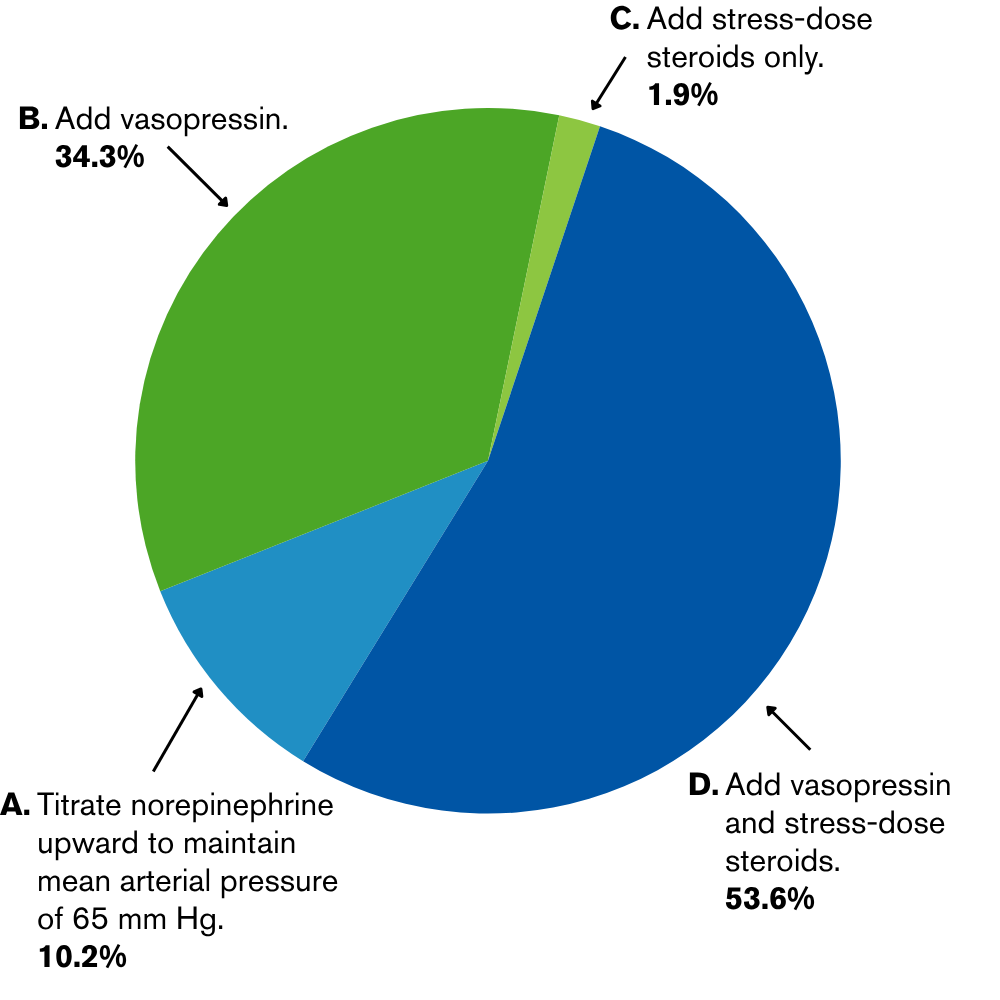
A 52-year-old woman presents to the emergency department with a 1- to 2-day history of fever, right flank pain, and nausea. Vital signs are as follows: temperature 39.1 °C (102.4 °F), heart rate 130 beats/min, respiratory rate 22 breaths/min, and blood pressure 70/40 mm Hg. She has right costovertebral angle tenderness. Laboratory findings are as follows: WBCs 15 × 103/μL, creatinine 1.9 mg/dL, and lactate 3.5 mmol/L. Urinalysis reveals many WBCs and few RBCs. CT reveals right hydronephrosis with an obstructing ureteral stone. She receives 2 L lactated Ringer solution and is started on norepinephrine and broad-spectrum antibiotics. Blood and urine cultures are pending. Urology plans intervention once the patient is stabilized. Despite increasing norepinephrine to 0.25 µg/kg/min, blood pressure remains low at 80/50 mm Hg.
Which of the following is the most appropriate next step?
Here’s how your peers responded:
Read the research: Clinicians Corner: Practical Tips for Clinical Stabilization in Septic Shock

